Things You Should Know
What does PMOS fundamentally describe?
Polyendocrine Metabolic Ovarian Syndrome (PMOS) is a newer term for what was long called Polycystic Ovary Syndrome (PCOS). The newer name reflects a broader view: this is not only an ovarian or fertility condition, but a multisystem endocrine and metabolic syndrome. Available scientific literature describes overlapping reproductive, metabolic, inflammatory, cardiovascular, and psychological features.
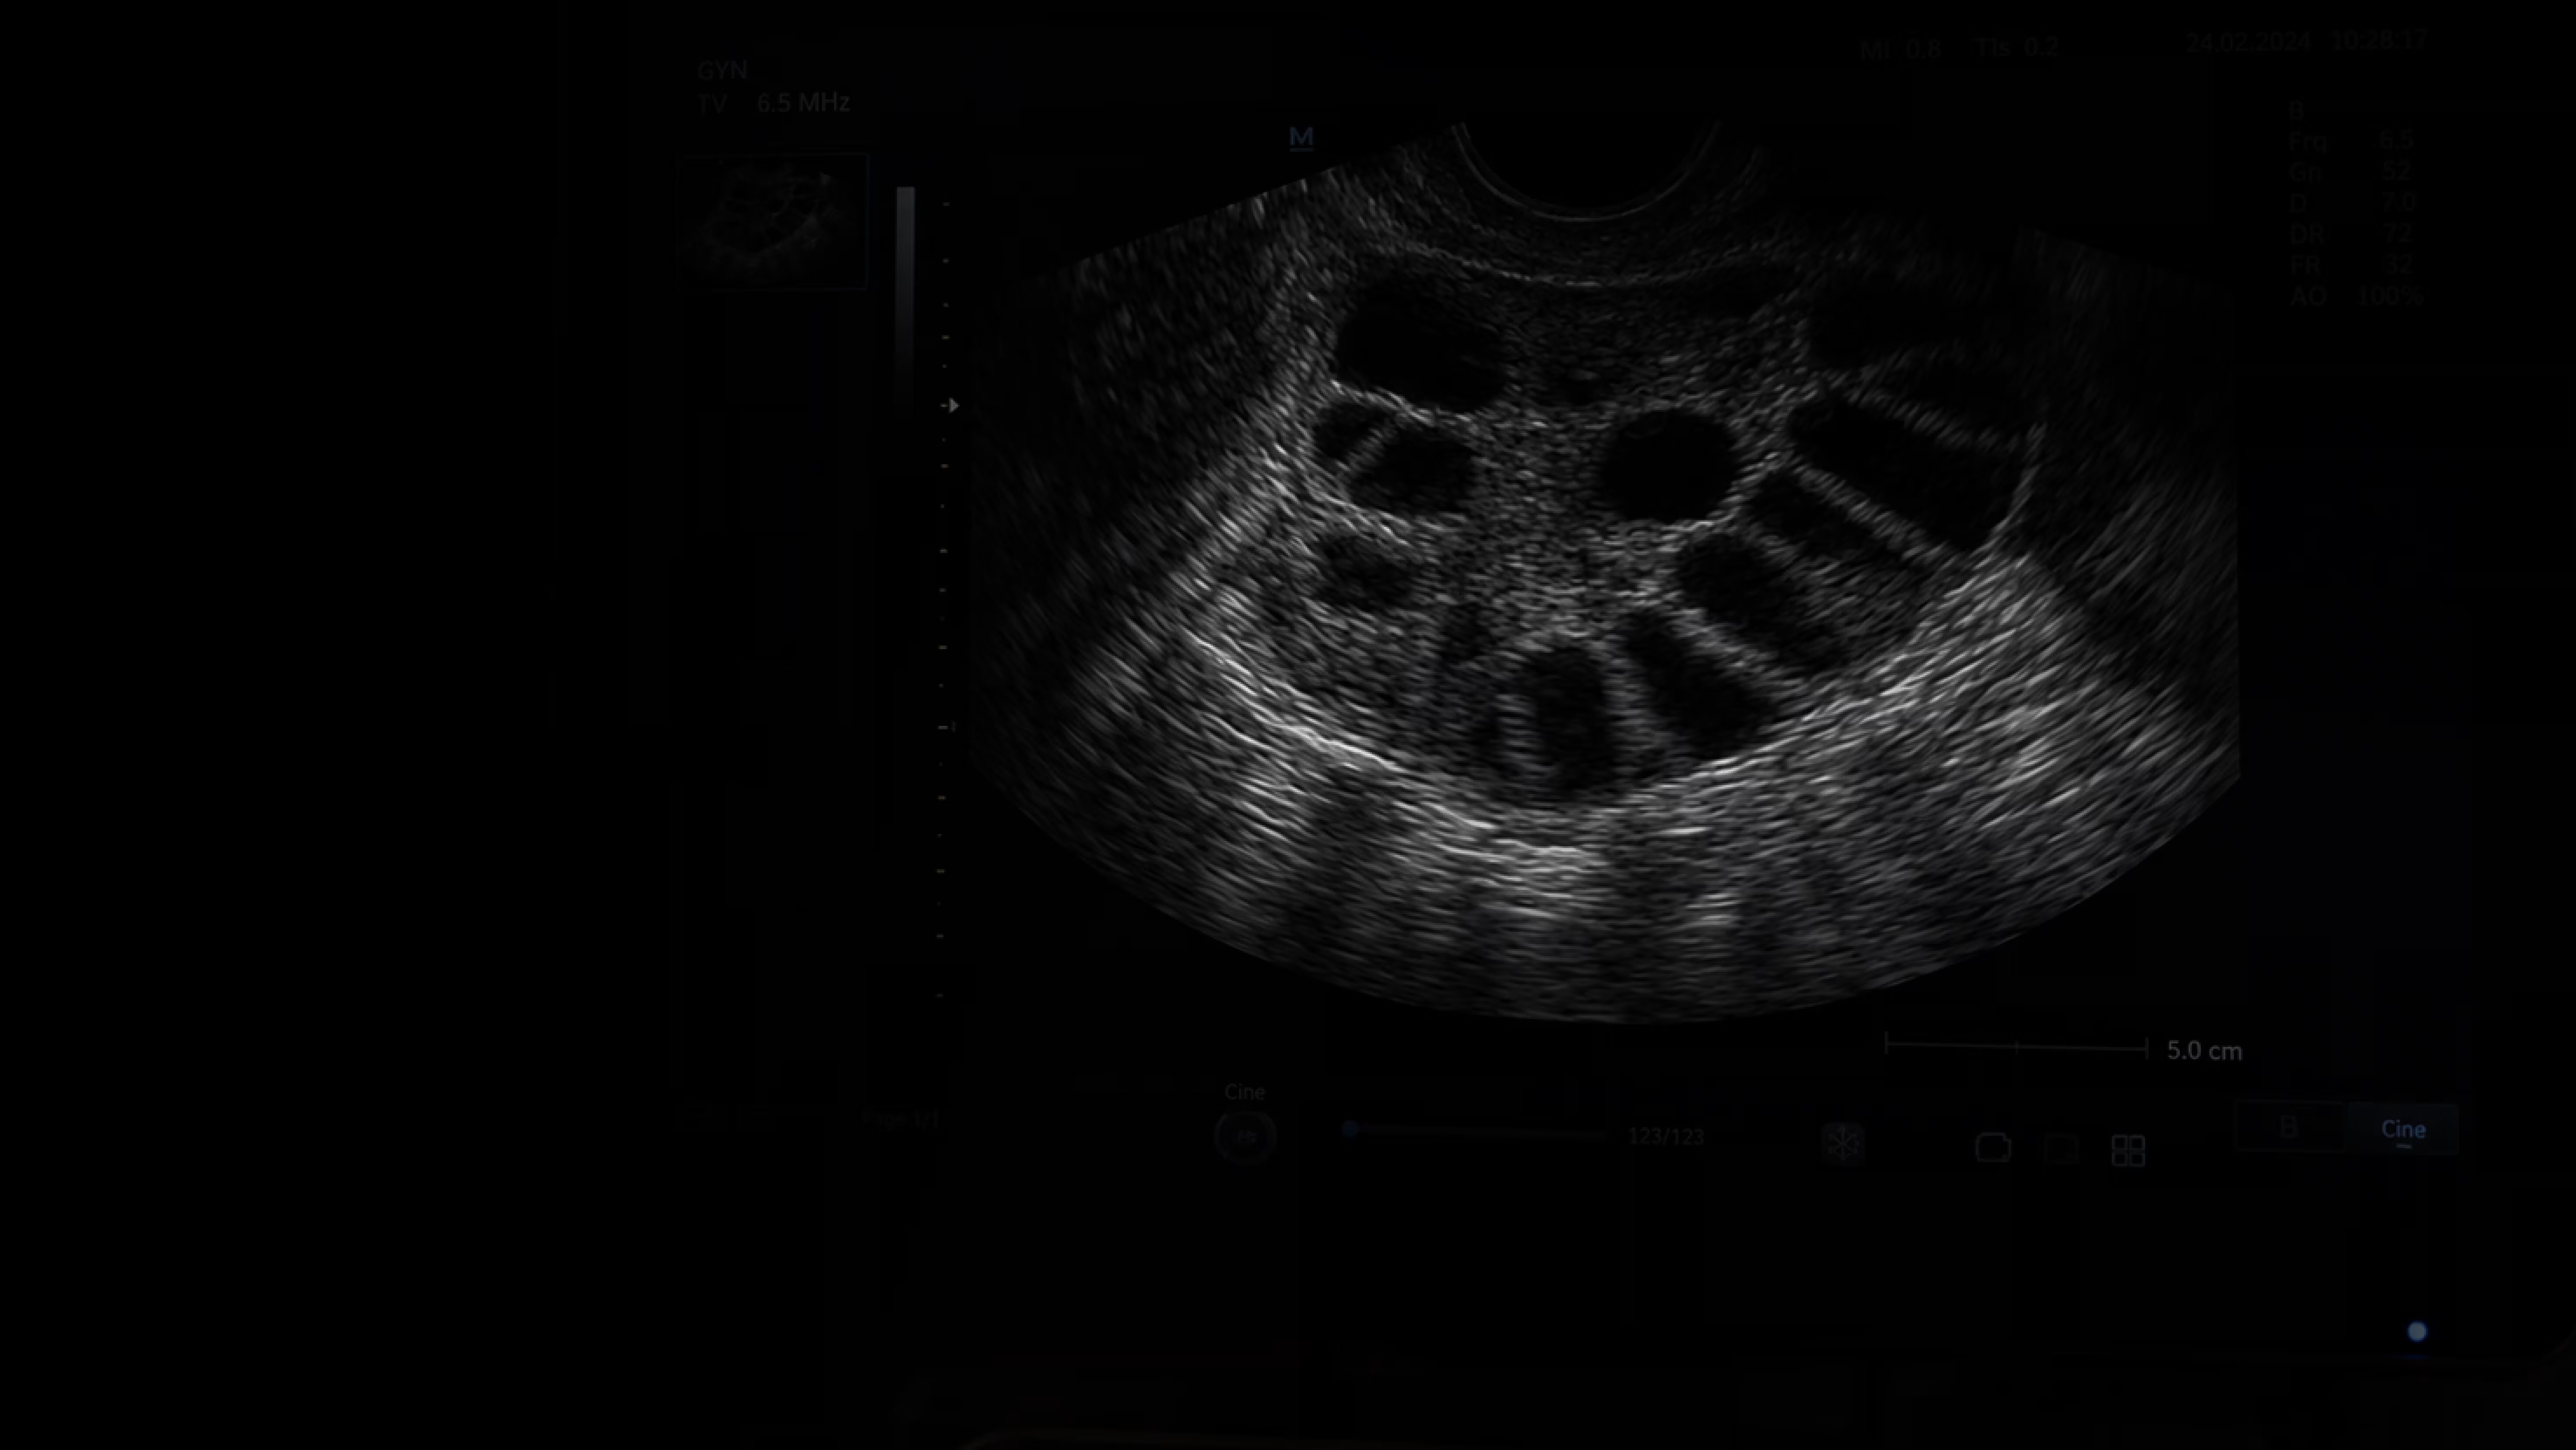
In human clinical research, the core diagnostic framework still centers on at least two of three findings: ovulatory dysfunction, hyperandrogenism, and polycystic ovarian morphology (PCOM). Ovulatory dysfunction means irregular or absent ovulation. Hyperandrogenism means excess androgen hormones, measured clinically or biochemically. Polycystic ovarian morphology (PCOM) refers to a characteristic ultrasound pattern and does not diagnose the syndrome by itself.
The reason this redefinition matters is conceptual as well as practical. It better captures metabolic overlap, including insulin resistance, dyslipidemia, obesity in some patients, and chronic low-grade inflammation. It also fits the marked heterogeneity seen across phenotypes, ethnic groups, and life stages. The evidence base includes human consensus papers, clinical reviews, and observational studies, but debate remains about ideal diagnostic thresholds, especially for androgen testing and ultrasound criteria.
Why does PMOS matter for healthy aging?
PMOS matters for longevity because its effects may extend far beyond menstrual patterns or fertility concerns. Human observational studies and long-term follow-up studies link PMOS with higher rates of insulin resistance, impaired glucose regulation, dyslipidemia, hypertension, metabolic syndrome (MetS), and greater cardiometabolic burden in at least some subgroups. These factors are strongly relevant to aging because they are associated with later cardiovascular disease and type 2 diabetes mellitus (T2DM).
The key point is not that every person with PMOS will develop these outcomes. Rather, the syndrome appears to shift risk upward, especially when obesity, visceral adiposity, or persistent hyperandrogenism are present. One human follow-up study over about ten years reported strong correlations between earlier and later metabolic parameters, suggesting that risk patterns may persist across decades. That does not prove inevitable progression, but it supports early risk awareness.
Longevity also includes mental and social health. Reviews of human evidence describe higher rates of anxiety, depression, and reduced quality of life in affected women. These burdens can influence sleep, physical activity, healthcare access, and long-term self-care. In this way, PMOS relates to healthy aging through cumulative metabolic, vascular, reproductive, and psychosocial pathways rather than through one isolated symptom.
Which basic terms help explain metabolic overlap?
Several terms make PMOS easier to understand. Insulin resistance (IR) means body tissues respond less effectively to insulin, so the body often compensates by producing more insulin. In human studies, this higher insulin state is associated with greater ovarian androgen production and lower Sex Hormone-Binding Globulin (SHBG), which can increase biologically active androgens.
Hyperandrogenism means excess androgen activity. It may appear clinically as acne or increased terminal hair growth, and biochemically through hormone testing. Luteinizing Hormone (LH) and Follicle-Stimulating Hormone (FSH) are pituitary signals that regulate ovarian function; a relative excess of Luteinizing Hormone (LH) may favor androgen production and impaired follicle maturation.
Metabolic overlap also includes dyslipidemia, meaning an unfavorable lipid profile, often with higher triglycerides and lower High-Density Lipoprotein (HDL). Chronic low-grade inflammation refers to persistent, modest immune activation, often tracked in studies with markers such as high-sensitivity C-Reactive Protein (hs-CRP). Some research also distinguishes Metabolically Healthy Obesity (MHO) from Metabolically Unhealthy Obesity (MUO). Human cross-sectional data suggest this distinction matters in PMOS, because people with similar body size may still differ substantially in inflammation, insulin resistance, liver fat markers, and cardiometabolic risk.
Who may benefit most from this knowledge?
The most direct beneficiaries are women of reproductive age with diagnosed or suspected PMOS, especially those with irregular cycles, signs of hyperandrogenism, obesity, insulin resistance, or a family history of type 2 diabetes mellitus (T2DM). Human studies suggest these features often cluster, although not every patient shows the same pattern. Lean individuals can also have significant metabolic dysfunction, so appearance alone may not reflect risk.
This knowledge is also relevant for adolescents and young adults. Symptoms may begin early, yet the metabolic consequences can unfold gradually. In human observational literature, early-life phenotype may shape later cardiometabolic burden, which is why understanding the syndrome as systemic rather than cosmetic or purely gynecologic has value.
Another group includes people planning pregnancy or already pregnant. Human studies associate PMOS with infertility and with pregnancy complications such as gestational diabetes and preeclampsia. Families may also care about possible intergenerational effects. A human individual participant data meta-analysis found subtle cardiometabolic differences in offspring of mothers with Polycystic Ovary Syndrome (PCOS), especially girls, but the findings were modest and not uniform across outcomes. That means concern is reasonable, but certainty about long-term causal effects remains limited.
In what situations is PMOS knowledge most important?
PMOS knowledge becomes especially important when symptoms seem unrelated but occur together. Examples include irregular periods, acne, increased hair growth, weight gain around the abdomen, elevated glucose, adverse lipid results, difficulty conceiving, or fatty liver markers. In these settings, a broader endocrine-metabolic lens may help explain why reproductive and metabolic findings often travel together.
It is also important when people assume that absence of severe obesity means low long-term risk. Human cross-sectional evidence shows that metabolic risk differs within body-size categories. For example, Metabolically Healthy Obesity (MHO) and Metabolically Unhealthy Obesity (MUO) do not carry the same profile. Research has linked the less favorable phenotype with higher inflammation, insulin, androgen levels, and cardiometabolic indices.
A third context involves emerging mechanisms, such as the gut–metabolism–endocrine–ovary axis. Reviews describe associations between gut microbiota dysbiosis, inflammation, insulin resistance, and androgen excess. However, much of this evidence is observational, short-term, or based on animal models. Human trials of probiotics, prebiotics, or microbiota-targeted strategies remain limited. So this area is scientifically interesting and may inform future longevity strategies, but many claimed benefits are still early rather than established.
Tell Me More
How do lifestyle habits and body fat patterns change PMOS risk?
Polyendocrine Metabolic Ovarian Syndrome (PMOS) does not interact with lifestyle through body weight alone. In a human cross-sectional study of 94 treatment-naive women with obesity and PMOS, the main outcomes included insulin, testosterone, high-sensitivity C-Reactive Protein (hs-CRP), Homeostatic Model Assessment of Insulin Resistance (HOMA-IR), Visceral Adiposity Index (VAI), Fatty Liver Index (FLI), and Mediterranean Diet (MD) adherence. Women with the Metabolically Unhealthy Obesity (MUO) phenotype had worse inflammatory, endocrine, and metabolic values than those with Metabolically Healthy Obesity (MHO), despite similar total energy intake. Lower adherence to the Mediterranean Diet (MD) was associated with the less favorable phenotype.
For longevity, this suggests that fat distribution, liver fat risk, and inflammatory pattern may matter as much as body mass itself. The available evidence is observational, so it cannot prove that diet pattern alone caused the difference. Still, it supports a broader aging strategy that tracks metabolic quality, not only size. Research and guidelines also continue to place lifestyle measures as foundational in PMOS because cardiometabolic strain may accumulate across decades.
How do medications fit into PMOS beyond symptom control?
Medication choice in Polyendocrine Metabolic Ovarian Syndrome (PMOS) often reflects the syndrome’s overlap between reproductive and metabolic health. Combined Oral Contraceptives (COCs) remain first-line treatment in many guidelines for menstrual irregularity and hyperandrogenic symptoms when pregnancy is not the immediate goal. Scientific reviews describe benefits through cycle regulation and androgen suppression, but some formulations may also affect cardiometabolic risk markers, so treatment is usually framed within an overall risk profile rather than as a cosmetic measure.
Metformin is the most widely used insulin-sensitizing drug in PMOS. Human clinical evidence and broader reviews associate it with improved insulin sensitivity, lower circulating insulin and androgen levels, and better menstrual regularity. Newer agents, such as Glucagon-Like Peptide-1 Receptor Agonists (GLP-1 receptor agonists), have shown short-term metabolic and weight-related benefits in clinical settings, especially in obesity-associated PMOS. Longevity relevance comes from the link between improved glucose-insulin biology and lower long-term cardiometabolic burden. However, evidence strength differs by drug class, and harms matter too: gastrointestinal side effects are common with metformin, and some hormonal therapies carry thrombotic considerations.
Is the gut microbiome a real target or still an early idea?
The gut angle is biologically plausible, but it is still an evolving area. Scientific reviews describe an integrated gut-metabolism-endocrine-ovary axis in Polyendocrine Metabolic Ovarian Syndrome (PMOS). Proposed mediators include Short-Chain Fatty Acids (SCFAs), Branched-Chain Amino Acids (BCAAs), bile acids, and Lipopolysaccharide (LPS). These pathways are linked with inflammation, insulin resistance, and androgen excess, all of which matter for long-term metabolic aging.
Still, the evidence is mixed in strength. Much of the mechanistic support comes from animal studies and associative human studies, not from large long-term randomized trials. Limited human studies suggest that probiotics, prebiotics, and inulin may improve insulin resistance, dyslipidemia, or hyperandrogenism, while Fecal Microbiota Transplantation (FMT) remains supported mainly by animal work and lacks human outcome evidence here. That distinction matters. The longevity assumption comes from the idea that reducing chronic inflammation and improving insulin signaling may support healthier aging, but this has not yet been established as a direct lifespan effect in PMOS trials.
What misconceptions about PMOS still interfere with healthy aging?
A common misconception is that Polyendocrine Metabolic Ovarian Syndrome (PMOS) is only a fertility or ovarian disorder. The scientific literature now frames it as a multisystem condition with metabolic, inflammatory, cardiovascular, and psychological dimensions. Another error is assuming that only people with obvious obesity face long-term risk. Human studies show that insulin resistance and dyslipidemia can occur even without severe obesity, while obesity itself is not viewed as the sole cause.
A third misconception is that all new findings are already clinically settled. They are not. For example, protein biomarkers, machine learning screening tools, and microbiome-targeted strategies are scientifically interesting, but many remain early-stage and need validation across diverse populations. Even the terminology shift from Polycystic Ovary Syndrome (PCOS) to Polyendocrine Metabolic Ovarian Syndrome (PMOS) is better understood as a change in disease framing, not as proof of a new disease entity. For longevity, the practical implication is restraint: broader monitoring of metabolic and psychological health is reasonable, but strong causal claims should wait for better long-term human evidence.
Level Up
How may early biology shape PMOS across the lifespan?
A more advanced view of Polyendocrine Metabolic Ovarian Syndrome (PMOS) treats it as a life-course condition, not only a reproductive diagnosis. Scientific reviews describe genetic susceptibility, altered steroid production, insulin signaling defects, and epigenetic programming as interacting layers. Epigenetic programming means chemical changes around genes that can alter gene activity without changing the DNA (deoxyribonucleic acid) sequence itself. One proposed model is that prenatal androgen exposure may bias later neuroendocrine, metabolic, and ovarian function in people who are already susceptible.
The longevity link is important. If early programming shifts insulin resistance, inflammation, or androgen balance upward, later risks may extend toward type 2 diabetes mellitus (T2DM), adverse lipid patterns, liver fat accumulation, and cardiovascular strain. Human evidence for this life-course view comes mainly from observational and follow-up studies, plus broader clinical reviews. These studies support association, not certainty. Animal studies add mechanistic support because prenatal hormone exposure can reproduce PMOS-like features, but animal models cannot capture the full human social and metabolic environment.
This framework may matter over the next decade because it could move care toward earlier phenotype recognition and longer cardiometabolic surveillance. Still, available evidence does not show that early biological markers alone can reliably predict each person’s aging trajectory.
Can diagnosis become more precise than current criteria?
Research suggests that diagnosis may become more layered, combining symptoms, imaging, metabolic markers, and computational tools. Current criteria remain useful, but they compress a very heterogeneous syndrome into a limited set of features. Human biomarker research in Polyendocrine Metabolic Ovarian Syndrome (PMOS) phenotype A, the subgroup with oligo-anovulation, hyperandrogenism, and polycystic ovarian morphology (PCOM), has identified circulating protein patterns linked with immune and metabolic pathways. These findings may eventually help separate severe phenotypes from healthy controls more consistently.
A second line of work involves machine learning (ML) and deep learning (DL). In a human systematic review and meta-analysis, the main outcomes were diagnostic sensitivity, specificity, diagnostic odds ratio, and summary receiver operating curve performance. Reported pooled diagnostic accuracy was high, especially in ultrasound-based models. For longevity, better diagnosis may matter because earlier recognition could support earlier cardiometabolic monitoring. However, that is still an indirect benefit, not a demonstrated aging outcome.
The limits are just as important as the promise. Biomarker studies used small case-control samples and often focused on phenotype A, which may overstate performance in broader populations. Machine learning (ML) studies also showed substantial heterogeneity and possible bias from study design, dataset quality, and limited external validation. So precision diagnosis is plausible, but not yet settled.
What advanced mechanisms connect PMOS to long-term health?
At a deeper level, Polyendocrine Metabolic Ovarian Syndrome (PMOS) appears to involve interacting control loops rather than one single defect. Reviews describe cross-talk among insulin resistance, ovarian androgen production, hypothalamic-pituitary-ovarian axis signaling, adipose tissue dysfunction, oxidative stress, and chronic low-grade inflammation. A control loop means one change feeds another, then that second change reinforces the first. For example, higher insulin may amplify ovarian androgen production, while androgen excess may worsen fat distribution and metabolic strain.
An additional layer involves mitochondria, the cell structures that help generate energy. Mitochondrial dysfunction is discussed in human reviews as a possible contributor to oxidative stress and impaired metabolic flexibility. This may help explain why some people develop broader cardiometabolic complications over time while others do not, even when outward reproductive features appear similar. Human evidence supports this mainly through mechanistic and clinical association data rather than long-term intervention trials.
For longevity, the main implication is that PMOS may accelerate exposure to pathways linked with vascular aging, glucose dysregulation, and fatty liver disease. That does not mean accelerated aging is proven in every patient. It means the syndrome may increase cumulative biological stress. Future best practice may therefore rely less on ovarian signs alone and more on integrated tracking of metabolic resilience across adulthood.
Where might PMOS science be in ten years?
The field is likely to move toward phenotype-based and systems-level models. In practice, that means Polyendocrine Metabolic Ovarian Syndrome (PMOS) may be classified less by a single label and more by clusters such as androgen-dominant, insulin-resistant, inflammation-linked, or microbiome-associated patterns. Scientific reviews and consensus work already point in this direction because current definitions do not fully capture ethnic diversity, life-stage differences, or metabolic heterogeneity.
Several research paths may shape that future. Human studies may refine multi-marker panels that combine hormones, metabolic signals, inflammatory markers, and imaging features. Machine learning (ML) may help standardize ultrasound interpretation and reduce observer variation. Longitudinal cohorts may clarify which early features best predict later diabetes, liver disease, or cardiovascular burden. Animal and mechanistic studies may continue to test microbiome, mitochondrial, and epigenetic pathways, but translation into human longevity outcomes will still require careful trials.
The most realistic forecast is not a single breakthrough, but better stratification. That matters for healthy aging because it may help match surveillance intensity to actual risk. Even so, published evidence still shows major gaps in long-term randomized trials, causal inference, and validation across diverse populations. So the next decade may bring clearer maps of risk more than definitive answers about prevention.
Pros and Cons
Pros
- Broader risk recognition
Human reviews and consensus papers suggest the PMOS framework better captures metabolic, inflammatory, and cardiovascular burden than an ovary-only label, which may support earlier long-term risk monitoring relevant to healthy aging.
- More inclusive diagnosis
Consensus and clinical reviews indicate the broader model may improve recognition across varied phenotypes, ethnic groups, and life stages, especially when reproductive signs coexist with insulin resistance, dyslipidemia, or obesity.
- Supports integrated care
Human guidelines and reviews describe benefit from linking gynecologic, endocrine, metabolic, and psychological management, which may improve cycle symptoms, fertility planning, and long-term cardiometabolic follow-up together.
- May reduce stigma
Consensus work suggests moving beyond the older name may reduce the narrow fertility-focused and cyst-focused framing, which could improve patient understanding, engagement, and psychosocial support over the lifespan.
- Targets longevity pathways
Human clinical literature links PMOS-aware management with attention to insulin resistance, adiposity, lipids, and inflammation, factors associated with later type 2 diabetes and cardiovascular disease rather than short-term symptoms alone.
Cons
- Diagnostic inconsistency
Human studies and reviews note that androgen testing, ultrasound thresholds, and phenotype definitions still vary. This can delay diagnosis, complicate comparison across clinics, and create uneven long-term surveillance.
- Heterogeneous risk profile
Not all patients show the same metabolic burden. Broad labeling may obscure meaningful differences between phenotypes, including lean and obesity-associated forms, which can limit precision in prognosis and management.
- Therapy trade-offs
Common management approaches improve some domains but may add burdens. Reviews note gastrointestinal effects with metformin, side effects with antiandrogens, and cardiometabolic considerations with some hormonal therapies.
- Limited long-term trials
Many supportive claims come from reviews, observational studies, or short-term trials. Long-term human evidence on whether newer PMOS-focused strategies alter aging-related outcomes remains limited.
- Resource-intensive model
A multisystem approach may require repeated hormonal, metabolic, imaging, and psychological assessment. This broader workup can increase cost, time, and access barriers, especially across lower-resource settings.
Considerations
- Evidence type varies
Some points are supported by human clinical studies and consensus documents, while gut microbiome, mitochondrial, and epigenetic pathways rely more on mechanistic, associative, or animal evidence than proven human aging outcomes.
- Phenotype matters
Research consistently describes PMOS as heterogeneous. Phenotypes A to D, body fat pattern, and insulin resistance status may shape reproductive and cardiometabolic burden, so averages may not fit each subgroup.
- Life-stage differences
Adolescence, reproductive years, pregnancy planning, and later adulthood may shift which features dominate. Available evidence suggests the same label can carry different fertility, metabolic, and psychosocial implications over time.
- Cultural context counts
Studies note that stigma, local norms around fertility, and regional access to testing can shape how PMOS is recognized and managed. The newer terminology may not yet be equally adopted across health systems.
- Emerging tools need validation
Protein biomarkers and machine learning models show promise for diagnosis in human research, but many studies used selected datasets or narrow phenotypes. External validation across diverse populations is still needed.
Actionable Intelligence
Summary
Log menstrual timing, acne, scalp hair shedding, and unwanted hair growth weekly for 8 to 12 weeks in a phone note or paper journal. This low-effort pattern tracking often helps connect hormone changes with metabolic shifts and supports earlier long-term risk discussions.
Scientific Connection
Clinical reviews and consensus papers describe PMOS as defined partly by ovulatory dysfunction and hyperandrogenism, so symptom pattern tracking can help flag multisystem changes relevant to long-term metabolic monitoring.
Evidence Snapshot
The evidence for symptom tracking is indirect but clinically practical. In the literature, diagnosis still relies heavily on patterns of irregular ovulation and androgen-related symptoms, so structured self-observation can make those patterns clearer over time.
Evidence Points
- Rotterdam-based diagnosis commonly uses at least two features: ovulatory dysfunction, hyperandrogenism, and polycystic ovarian morphology, so cycle and symptom logs can help capture two major clinical domains (Summaiya Banu, Polyendocrine metabolic ovarian syndrome: A comprehensive review of emerging pathophysiological and clinical perspectives).
- Reviews describe common manifestations such as menstrual irregularities, hirsutism (excess coarse hair growth), and acne, which are practical symptoms people can track week to week (Zainab Abd Alkathem Fatnan, Polycystic Ovary Syndrome (PCOS): Epidemiology, Pathophysiology, Clinical Management and Regional Perspectives from the Middle East and Iraq: A Narrative Literature Review).
- The syndrome is framed as heterogeneous across phenotypes and life stages, which supports repeated observation rather than one-time impression when thinking about long-term health patterns (Joycilene Garces Cantanhede, POLYENDOCRINE METABOLIC OVARIAN SYNDROME (PMOS): A GLOBAL CONSENSUS PROCESS AND SCIENTIFIC REDEFINITION).
Safety Note
This is not a prescription or diagnosis, and any change in your health routine or interpretation of symptoms should be discussed with a qualified clinician first.
References
Summaiya Banu — Polyendocrine metabolic ovarian syndrome: A comprehensive review of emerging pathophysiological and clinical perspectives
Zainab Abd Alkathem Fatnan — Polycystic Ovary Syndrome (PCOS): Epidemiology, Pathophysiology, Clinical Management and Regional Perspectives from the Middle East and Iraq: A Narrative Literature Review
Joycilene Garces Cantanhede — POLYENDOCRINE METABOLIC OVARIAN SYNDROME (PMOS): A GLOBAL CONSENSUS PROCESS AND SCIENTIFIC REDEFINITION
Scores
Score Explanation
This action scores lower than a broad syndrome-level longevity index because it is mainly a detection tool, not a treatment. The similarity is that both focus on long-term metabolic awareness. The difference is simple: better tracking can support earlier care, but it does not directly reduce insulin resistance or inflammation on its own.
Summary
Use a Mediterranean-style plate 5 to 7 days weekly: vegetables, legumes, whole grains, fish, nuts, fruit, and extra virgin olive oil. Track how many meals fit this pattern each week. In observational work, better adherence aligns with a healthier metabolic profile.
Scientific Connection
A cross-sectional human study linked lower Mediterranean Diet adherence with the metabolically unhealthy obesity phenotype, which showed worse insulin resistance, inflammation, androgen, and liver-fat-related markers in women with the syndrome.
Evidence Snapshot
Among everyday habits, dietary pattern has some of the clearest practical overlap with long-term metabolic aging in this condition. The strongest support here comes from observational human data plus broader reviews that place lifestyle change at the center of care.
Evidence Points
- In a cross-sectional study of 94 treatment-naive women with obesity and the syndrome, lower Mediterranean Diet adherence was associated with the metabolically unhealthy obesity phenotype (Luigi Barrea, Metabolically Healthy Obesity (MHO) vs. Metabolically Unhealthy Obesity (MUO) Phenotypes in PCOS: Association with Endocrine-Metabolic Profile, Adherence to the Mediterranean Diet, and Body Composition).
- The metabolically unhealthy phenotype showed worse insulin, testosterone, high-sensitivity C-reactive protein (hs-CRP: inflammation marker), Homeostatic Model Assessment of Insulin Resistance (HOMA-IR: insulin resistance estimate), Visceral Adiposity Index (VAI), and Fatty Liver Index (FLI) despite similar energy intake (Luigi Barrea, Metabolically Healthy Obesity (MHO) vs. Metabolically Unhealthy Obesity (MUO) Phenotypes in PCOS: Association with Endocrine-Metabolic Profile, Adherence to the Mediterranean Diet, and Body Composition).
- Reviews of gut and endocrine-metabolic pathways list Mediterranean-style eating among lifestyle approaches associated with improved metabolic, inflammatory, and reproductive outcomes (Shengyue Jin, Gut microbiota and polyendocrine metabolic ovarian syndrome: an integrated gut–metabolism–endocrine–ovary axis).
- Major clinical reviews describe lifestyle modification as foundational therapy because PMOS carries insulin resistance, dyslipidemia, inflammation, and cardiovascular overlap across adulthood (Summaiya Banu, Polyendocrine metabolic ovarian syndrome: A comprehensive review of emerging pathophysiological and clinical perspectives).
Safety Note
This is not a prescription or diagnosis, and any meaningful dietary change, especially if you have diabetes, gastrointestinal disease, or are pregnant, should be discussed with a qualified clinician first.
References
Luigi Barrea — Metabolically Healthy Obesity (MHO) vs. Metabolically Unhealthy Obesity (MUO) Phenotypes in PCOS: Association with Endocrine-Metabolic Profile, Adherence to the Mediterranean Diet, and Body Composition
Shengyue Jin — Gut microbiota and polyendocrine metabolic ovarian syndrome: an integrated gut–metabolism–endocrine–ovary axis
Summaiya Banu — Polyendocrine metabolic ovarian syndrome: A comprehensive review of emerging pathophysiological and clinical perspectives
Scores
Score Explanation
This score is close to a general longevity index because food pattern affects several aging-related pathways at once, especially insulin resistance and inflammation. It may score a bit lower than broader lifestyle claims because PMOS-specific proof is stronger for association than for long-term randomized causal benefit, even though the overall direction is favorable.
Summary
Do planned exercise 3 to 5 times weekly and log minutes completed. Options already described in the literature include aerobic training, intervals, or yoga. The common thread is consistency, because repeated movement is tied to better metabolic and inflammatory function over time.
Scientific Connection
Reviews of PMOS management place exercise inside first-line lifestyle care, and gut-metabolism literature lists aerobic training, high-intensity intervals, and yoga as approaches linked with improved metabolic and reproductive outcomes.
Evidence Snapshot
Exercise is one of the most practical longevity-linked actions in PMOS because it targets the syndrome’s metabolic side, not just symptoms. The exact best format is less settled than the broad message that regular movement matters.
Evidence Points
- Lifestyle intervention combining diet and exercise is described as first-line treatment to improve metabolic health in women with the syndrome (Alexandra Dietz de Loos, Metabolic health during a randomized controlled lifestyle intervention in women with PCOS).
- A review of the gut–metabolism–endocrine–ovary axis specifically lists aerobic training, high-intensity interval training, and yoga among lifestyle approaches that improve metabolic, inflammatory, and reproductive outcomes (Shengyue Jin, Gut microbiota and polyendocrine metabolic ovarian syndrome: an integrated gut–metabolism–endocrine–ovary axis).
- Broad clinical reviews describe lifestyle modification as foundational because insulin resistance, dyslipidemia, inflammation, and cardiovascular risk are central to PMOS (Summaiya Banu, Polyendocrine metabolic ovarian syndrome: A comprehensive review of emerging pathophysiological and clinical perspectives).
Safety Note
This is not a prescription or diagnosis, and any exercise change should be discussed with a qualified clinician first if you have major symptoms, pregnancy-related concerns, or other medical limits.
References
Alexandra Dietz de Loos — Metabolic health during a randomized controlled lifestyle intervention in women with PCOS
Shengyue Jin — Gut microbiota and polyendocrine metabolic ovarian syndrome: an integrated gut–metabolism–endocrine–ovary axis
Summaiya Banu — Polyendocrine metabolic ovarian syndrome: A comprehensive review of emerging pathophysiological and clinical perspectives
Scores
Score Explanation
This action sits near the high end because it targets the same long-term risk pathways that drive the condition’s aging relevance: glucose control, inflammation, and cardiovascular strain. Compared with a broad longevity index, safety may be slightly more conditional because exercise intensity and symptom burden differ from person to person.
Summary
Measure waist size and blood pressure at home once weekly for 8 weeks, using the same time of day when possible. Log trends, not single readings. This can help spot central fat pattern and vascular strain early, both linked with long-term cardiometabolic aging.
Scientific Connection
Human studies describe elevated blood pressure and increased waist circumference as common metabolic features in the syndrome and part of metabolic syndrome severity, a practical way to follow cardiometabolic burden over time.
Evidence Snapshot
This is a simple home-monitoring step with strong clinical logic. PMOS is tied to later cardiometabolic disease risk, and waist pattern plus blood pressure are easy real-world markers of that burden.
Evidence Points
- Women with the syndrome often show elevated blood pressure and increased waist circumference, two major components of metabolic syndrome (Alexandra Dietz de Loos, Metabolic health during a randomized controlled lifestyle intervention in women with PCOS).
- The continuous metabolic syndrome severity z-score is used to track change over time, underscoring that clustered metabolic markers matter as trends rather than isolated numbers (Alexandra Dietz de Loos, Metabolic health during a randomized controlled lifestyle intervention in women with PCOS).
- A systematic review and meta-analysis links the syndrome with long-term cardiometabolic outcomes including hypertension, type 2 diabetes, and dyslipidaemia (Vincent Wekker, Long-term cardiometabolic disease risk in women with PCOS: a systematic review and meta-analysis).
- Reviews also emphasize visceral fat pattern and cardiometabolic risk rather than appearance alone, supporting routine attention to abdominal fat distribution and pressure load (Zainab Abd Alkathem Fatnan, Polycystic Ovary Syndrome (PCOS): Epidemiology, Pathophysiology, Clinical Management and Regional Perspectives from the Middle East and Iraq: A Narrative Literature Review).
Safety Note
This is not a prescription or diagnosis, and any home trend suggesting persistently high blood pressure or rapid body changes should be discussed with a qualified clinician first.
References
Alexandra Dietz de Loos — Metabolic health during a randomized controlled lifestyle intervention in women with PCOS
Vincent Wekker — Long-term cardiometabolic disease risk in women with PCOS: a systematic review and meta-analysis
Zainab Abd Alkathem Fatnan — Polycystic Ovary Syndrome (PCOS): Epidemiology, Pathophysiology, Clinical Management and Regional Perspectives from the Middle East and Iraq: A Narrative Literature Review
Scores
Score Explanation
Compared with an overall longevity index, this rates lower because it is a monitoring habit, not a treatment. Still, it aligns closely with the syndrome’s aging story: blood pressure and abdominal fat pattern are practical windows into future cardiometabolic burden, so the action supports prevention through earlier visibility.
Summary
Arrange a clinician discussion when periods are irregular, insulin resistance is suspected, or family history of type 2 diabetes is present. Bring 3 months of cycle and symptom notes. The aim is timely glucose-risk review, since PMOS often overlaps with impaired insulin handling across adulthood.
Scientific Connection
Reviews identify insulin resistance as central in 65 to 70 percent of affected individuals and link PMOS with impaired glucose tolerance, type 2 diabetes, and metabolic syndrome, supporting earlier risk review in higher-risk subgroups.
Evidence Snapshot
Glucose-risk review is one of the most important long-term actions because insulin resistance sits near the center of PMOS biology. The exact test timing is individualized, but the rationale for earlier attention is well supported.
Evidence Points
- A major review reports insulin resistance in 65 to 70 percent of affected individuals, describing it as central to androgen excess and broader metabolic dysfunction (Summaiya Banu, Polyendocrine metabolic ovarian syndrome: A comprehensive review of emerging pathophysiological and clinical perspectives).
- Narrative clinical literature lists impaired glucose tolerance and elevated risk of type 2 diabetes among common long-term metabolic features (Zainab Abd Alkathem Fatnan, Polycystic Ovary Syndrome (PCOS): Epidemiology, Pathophysiology, Clinical Management and Regional Perspectives from the Middle East and Iraq: A Narrative Literature Review).
- A systematic review and meta-analysis focused on long-term cardiometabolic disease risk includes type 2 diabetes as a key downstream outcome associated with the syndrome (Vincent Wekker, Long-term cardiometabolic disease risk in women with PCOS: a systematic review and meta-analysis).
Safety Note
This is not a prescription or diagnosis, and any decision about glucose testing or interpretation of results should be discussed with a qualified clinician first.
References
Summaiya Banu — Polyendocrine metabolic ovarian syndrome: A comprehensive review of emerging pathophysiological and clinical perspectives
Zainab Abd Alkathem Fatnan — Polycystic Ovary Syndrome (PCOS): Epidemiology, Pathophysiology, Clinical Management and Regional Perspectives from the Middle East and Iraq: A Narrative Literature Review
Vincent Wekker — Long-term cardiometabolic disease risk in women with PCOS: a systematic review and meta-analysis
Scores
Score Explanation
This action can score as high as, or sometimes higher than, a broad longevity index because insulin resistance is such a central driver of later disease in PMOS. The difference is that benefit depends on follow-through after the review; the discussion itself opens the door, but does not by itself fix metabolic dysfunction.
Summary
Discuss lipid testing timing with a clinician if you have PMOS plus irregular cycles, insulin resistance, or family cardiometabolic history. Keep a simple record of each result over time. PMOS commonly overlaps with high triglycerides and lower protective cholesterol, which matter for vascular aging.
Scientific Connection
Clinical reviews and meta-analytic work connect PMOS with dyslipidemia, including higher triglycerides and lower high-density lipoprotein, making periodic lipid trend review relevant for cardiovascular aging surveillance.
Evidence Snapshot
Lipid review matters because PMOS is not just about ovaries or fertility. It often travels with an unfavorable cholesterol and triglyceride pattern that can quietly shape long-term heart and vessel risk.
Evidence Points
- Reviews describe dyslipidemia in PMOS as elevated triglycerides, increased low-density lipoprotein, reduced high-density lipoprotein, and altered particle size, all relevant to cardiovascular risk (Summaiya Banu, Polyendocrine metabolic ovarian syndrome: A comprehensive review of emerging pathophysiological and clinical perspectives).
- A systematic review and meta-analysis on long-term cardiometabolic disease risk includes serum lipids such as total cholesterol, low-density lipoprotein cholesterol, high-density lipoprotein cholesterol, and triglycerides as core outcomes (Vincent Wekker, Long-term cardiometabolic disease risk in women with PCOS: a systematic review and meta-analysis).
- Narrative clinical literature lists dyslipidemia as a frequent metabolic feature and part of the syndrome’s long-term cardiovascular complication profile (Zainab Abd Alkathem Fatnan, Polycystic Ovary Syndrome (PCOS): Epidemiology, Pathophysiology, Clinical Management and Regional Perspectives from the Middle East and Iraq: A Narrative Literature Review).
Safety Note
This is not a prescription or diagnosis, and testing intervals or any response to lipid results should be discussed with a qualified clinician first.
References
Summaiya Banu — Polyendocrine metabolic ovarian syndrome: A comprehensive review of emerging pathophysiological and clinical perspectives
Vincent Wekker — Long-term cardiometabolic disease risk in women with PCOS: a systematic review and meta-analysis
Zainab Abd Alkathem Fatnan — Polycystic Ovary Syndrome (PCOS): Epidemiology, Pathophysiology, Clinical Management and Regional Perspectives from the Middle East and Iraq: A Narrative Literature Review
Scores
Score Explanation
This score is slightly lower than actions that directly change behavior because it is mostly a monitoring step. Still, it closely matches the broader longevity picture: PMOS often includes a lipid pattern that raises cardiovascular concern over time, so regular review supports earlier prevention rather than symptom-only care.
Summary
Set a weekly 10-minute check-in for mood, sleep, stress, and daily functioning for at least 6 weeks. If symptoms keep interfering with life, bring the notes to a clinician or therapist. Psychological strain is common in PMOS and can quietly worsen long-term self-care and metabolic health.
Scientific Connection
Reviews consistently describe depression, anxiety, and quality-of-life burden as common in PMOS, and comprehensive management frameworks include psychological screening and support alongside metabolic and reproductive care.
Evidence Snapshot
Mental health is a real part of PMOS, not a side note. This matters for longevity because mood and stress can shape sleep, activity, eating patterns, and follow-through on long-term metabolic care.
Evidence Points
- Comprehensive reviews identify depression and anxiety as common in PMOS and link these disturbances to hormonal imbalance and metabolic dysfunction (Summaiya Banu, Polyendocrine metabolic ovarian syndrome: A comprehensive review of emerging pathophysiological and clinical perspectives).
- Narrative clinical literature notes notably elevated depression and anxiety burden with quality-of-life effects in affected women (Zainab Abd Alkathem Fatnan, Polycystic Ovary Syndrome (PCOS): Epidemiology, Pathophysiology, Clinical Management and Regional Perspectives from the Middle East and Iraq: A Narrative Literature Review).
- Holistic management frameworks explicitly include psychological screening and support as essential components of care rather than optional add-ons (Summaiya Banu, Polyendocrine metabolic ovarian syndrome: A comprehensive review of emerging pathophysiological and clinical perspectives).
Safety Note
This is not a prescription or diagnosis, and persistent low mood, anxiety, or thoughts of self-harm require prompt discussion with a qualified clinician or mental health professional first.
References
Summaiya Banu — Polyendocrine metabolic ovarian syndrome: A comprehensive review of emerging pathophysiological and clinical perspectives
Zainab Abd Alkathem Fatnan — Polycystic Ovary Syndrome (PCOS): Epidemiology, Pathophysiology, Clinical Management and Regional Perspectives from the Middle East and Iraq: A Narrative Literature Review
Scores
Score Explanation
This action may score a little lower than a broad medical longevity index because its effects are often indirect rather than immediately metabolic. Still, the overlap is strong: anxiety, depression, and stress can erode sleep, exercise consistency, and healthcare follow-through, so addressing them can meaningfully support long-term healthy aging.
Summary
If you are using hormonal or metabolic medicines, review benefits, side effects, and goals with a clinician at routine follow-up. Bring notes on cycle regularity, skin changes, stomach side effects, and energy. In PMOS, drug choice often depends on whether the main target is cycle control, androgen symptoms, or metabolism.
Scientific Connection
Clinical reviews describe combined oral contraceptives for menstrual and androgen symptoms and metformin or newer metabolic agents for insulin resistance; benefit depends on the symptom profile, metabolic risk, and tolerance.
Evidence Snapshot
Medication can be helpful in PMOS, but the literature treats it as targeted support rather than one-size-fits-all care. Matching the medicine to the dominant problem is what makes this review step useful.
Evidence Points
- Combined oral contraceptives are described as first-line treatment in many guidelines for menstrual irregularity and hyperandrogenic symptoms when pregnancy is not the immediate goal (Zainab Abd Alkathem Fatnan, Polycystic Ovary Syndrome (PCOS): Epidemiology, Pathophysiology, Clinical Management and Regional Perspectives from the Middle East and Iraq: A Narrative Literature Review).
- Metformin is widely used for metabolic effects, with literature linking it to improved insulin sensitivity, lower circulating insulin and androgen levels, and better menstrual regularity (Summaiya Banu, Polyendocrine metabolic ovarian syndrome: A comprehensive review of emerging pathophysiological and clinical perspectives).
- Newer agents including glucagon-like peptide-1 receptor agonists are described as promising for metabolic dysfunction, but evidence strength differs across drug classes and long-term data are still developing (Summaiya Banu, Polyendocrine metabolic ovarian syndrome: A comprehensive review of emerging pathophysiological and clinical perspectives).
- Reviews also note side effects and risk tradeoffs, including gastrointestinal effects with metformin and thrombotic considerations with some hormonal therapies, which supports regular fit-and-tolerance review (tell_me_more synthesis grounded in PMOS studies).
Safety Note
This is not a prescription or diagnosis; if you are using any medicine or supplement, do not start, stop, or change it without discussing it with a qualified clinician first.
References
Zainab Abd Alkathem Fatnan — Polycystic Ovary Syndrome (PCOS): Epidemiology, Pathophysiology, Clinical Management and Regional Perspectives from the Middle East and Iraq: A Narrative Literature Review
Summaiya Banu — Polyendocrine metabolic ovarian syndrome: A comprehensive review of emerging pathophysiological and clinical perspectives
Scores
Score Explanation
This action can approach the broader longevity index in impact because medicines may directly change major pathways like insulin resistance or androgen excess. Safety is lower, though, because benefit depends on the specific drug, side effects, and follow-up. That makes it more powerful than tracking alone, but also more conditional.
Summary
If digestive symptoms, insulin resistance, or repeated diet setbacks are part of your picture, discuss food-based gut support and whether probiotics or prebiotics fit your care plan. In PMOS, this area is promising but still early, so treat it as an adjunct, not a main therapy.
Scientific Connection
Gut–metabolism reviews link microbiota imbalance with inflammation, insulin resistance, and androgen excess in PMOS, but much of the intervention evidence comes from animal models or limited human studies rather than long-term trials.
Evidence Snapshot
Gut-targeted care is one of the most interesting newer areas in PMOS, but it is not yet one of the most settled. The practical takeaway is cautious optimism: supportive, not definitive.
Evidence Points
- Reviews describe gut microbiota dysbiosis as part of a self-reinforcing cycle involving inflammation, insulin resistance, hyperandrogenism, and ovarian dysfunction (Shengyue Jin, Gut microbiota and polyendocrine metabolic ovarian syndrome: an integrated gut–metabolism–endocrine–ovary axis).
- Microbiota-derived compounds such as short-chain fatty acids help maintain gut barrier integrity and improve insulin sensitivity, while lipopolysaccharide promotes inflammation and insulin resistance (Shengyue Jin, Gut microbiota and polyendocrine metabolic ovarian syndrome: an integrated gut–metabolism–endocrine–ovary axis).
- Limited evidence suggests probiotics and prebiotics may help restore microbial balance and improve insulin sensitivity, but fecal microbiota transplantation lacks human clinical outcome data here (Shengyue Jin, Gut microbiota and polyendocrine metabolic ovarian syndrome: an integrated gut–metabolism–endocrine–ovary axis).
- The same review notes that much of this field remains associative or based on animal and small human studies, so confidence is lower than for standard lifestyle care (Shengyue Jin, Gut microbiota and polyendocrine metabolic ovarian syndrome: an integrated gut–metabolism–endocrine–ovary axis).
Safety Note
This is not a prescription or diagnosis; if you are considering any probiotic, prebiotic, or other gut-focused product, discuss it with a qualified clinician first, especially if you are pregnant, immunocompromised, or taking other treatments.
References
Shengyue Jin — Gut microbiota and polyendocrine metabolic ovarian syndrome: an integrated gut–metabolism–endocrine–ovary axis
Scores
Score Explanation
This action scores clearly below the broader longevity picture because the mechanism is plausible but the human evidence is still early. The similarity is that it targets inflammation and insulin signaling, both relevant to aging. The difference is confidence: gut support looks promising as an add-on, but not yet as a core longevity strategy in PMOS.
Innovative Tips
- Myo-Inositol Trial
Human trials used 2-4 g/day for 8-12 weeks; early adjunct evidence, not settled.
- Omega-3 Window
Human studies examined daily omega-3 for 8-12 weeks; may support lipids, evidence mixed.
- Vitamin D Recheck
If deficient, studies examined repletion over 8-12 weeks; benefit may reflect correction.
- GLP-1 Tracking
Human use is clinical, not DIY; short-term metabolic effects noted, harms need review.
- Probiotic Phase
Small human studies tested daily use for 8-12 weeks; gut benefits remain early.
- Prebiotic Fiber Block
Early human work used daily prebiotics for 8-12 weeks; GI tolerance can vary.
- Polyphenol Add-On
Mechanistic and early human data support 8-12 week trials; outcomes stay uncertain.
- FMT Research Only
Mostly animal evidence; human benefit in PMOS is not established, so research only.
- Mediterranean Precision
Human observational data link sustained weekly adherence with healthier metabolic profiles.
- Biomarker Panel Watch
Protein panels are human diagnostic research, not self-care; validation is still limited.
Convergent and Divergent Viewpoints
Convergents
- PMOS is a multisystem syndrome with aging relevance
Consensus from reviews and global statements: PMOS extends beyond ovaries to metabolic, inflammatory, cardiovascular, and psychosocial domains tied to later healthspan. Evidence: human reviews and consensus papers.
- Insulin resistance is a central organizing feature
Human review evidence consistently places insulin resistance near the core; about 65-70% are affected in cited literature. It is linked with hyperinsulinemia, lower SHBG, androgen excess, and later diabetes risk.
- Hyperandrogenism and ovulatory dysfunction remain core human features
Across human clinical literature, excess androgen activity and impaired ovulation remain defining features, even under the broader PMOS model. This supports long-term monitoring beyond fertility alone.
- Chronic low-grade inflammation and oxidative stress matter
Available evidence broadly agrees these pathways are associated with metabolic dysfunction and higher cardiometabolic burden in PMOS. Evidence base: mainly human reviews, supported by mechanistic studies.
- Phenotypic heterogeneity is established, not a minor detail
Human studies consistently describe phenotypes A-D and marked variation by adiposity, insulin resistance, ethnicity, and life stage. This matters for prognosis and for interpreting longevity risk patterns.
- Rotterdam-based diagnosis remains the main clinical anchor
Strong practice-level agreement supports using at least 2 of 3 features: ovulatory dysfunction, hyperandrogenism, and PCOM. Human consensus and review evidence note it is widely used, though still refined.
- Lifestyle intervention is the foundation of management
Human guidelines, reviews, and trials consistently place diet and physical activity first because they may improve insulin sensitivity, adiposity, and metabolic burden without sacrificing future health.
- Long-term cardiometabolic surveillance is justified
Experts broadly agree PMOS warrants ongoing attention to glucose, lipids, blood pressure, and central adiposity because these factors track with later vascular and metabolic disease. Evidence: human observational and review data.
- Psychological burden is clinically relevant
Human reviews consistently report higher anxiety, depression, and reduced quality of life in many affected women. This is relevant to longevity through sleep, adherence, and cumulative self-care burden.
- Gut microbiome involvement is plausible but still early
There is broad agreement that dysbiosis is associated with PMOS biology, but demonstrated human outcome benefits remain limited. Evidence: associative human studies plus animal and mechanistic work.
Divergent
- Whether PMOS should fully replace PCOS in routine practice
Some researchers say the new term better reflects systemic aging-related risk; others say adoption is premature until criteria, coding, and local implementation are more uniform. Debate is conceptual and practical, not trivial.
- How hyperandrogenism should be measured
Some researchers favor broader clinical signs plus routine biochemistry; others stress assay variability and want stricter biochemical methods. The disagreement affects who is diagnosed and how risk is stratified.
- Ultrasound and PCOM thresholds remain contested
Some researchers argue current imaging thresholds overclassify younger women; others argue narrower cutoffs miss real cases. Debate centers on machine settings, operator variation, and age-related morphology.
- How much weight to give metabolic markers in diagnosis
Some say insulin, lipids, hs-CRP, or liver-fat proxies should complement core criteria; others say evidence is not mature enough for formal diagnostic inclusion. This affects early longevity-focused risk detection.
- Risk in lean versus obesity-associated phenotypes
Some researchers argue lean PMOS can still carry substantial hidden metabolic risk; others say average long-term burden is lower than in visceral-obesity phenotypes. The disagreement is about magnitude, not existence.
- Best medication path for obesity-linked metabolic dysfunction
Some researchers prioritize metformin as the established first metabolic drug; others favor growing use of GLP-1 receptor agonists in selected patients. Debate reflects trial length, cost, tolerability, and outcome scope.
- How far to extend anti-obesity pharmacotherapy
Some say newer weight-loss drugs may shift long-term cardiometabolic risk meaningfully; others say PMOS-specific long-term human data are still too short to justify broad enthusiasm. Evidence is evolving.
- Role of nutraceuticals as adjuncts
Some researchers support myo-inositol, omega-3, or vitamin D in selected settings; others note mixed trials, short follow-up, and product-quality variability. Benefits may reflect deficiency correction rather than added longevity gain.
- How actionable the gut-targeted treatment model is
Some researchers view probiotics or prebiotics as promising adjuncts; others argue human evidence is too small and associative, while FMT remains research-oriented. The divide reflects causality and durability concerns.
- How precise new diagnostic tools really are
Some researchers see protein biomarkers and machine learning as a path to earlier, more consistent diagnosis; others caution that small samples, phenotype bias, and limited external validation may overstate performance.
Longevity Index
85/100
Definition
- Polyendocrine Metabolic Ovarian Syndrome (PMOS)
The newer term for what was long called Polycystic Ovary Syndrome (PCOS). The newer name reflects a broader view: this is not only an ovarian or fertility condition, but a multisystem endocrine and metabolic syndrome.
- Polycystic Ovary Syndrome (PCOS)
The older name for PMOS, a condition now framed in the literature as a multisystem disorder rather than only an ovarian or fertility problem.
- Ovulatory dysfunction
Irregular or absent ovulation.
- Hyperandrogenism
Excess androgen activity. It may appear clinically as acne or increased terminal hair growth, and biochemically through hormone testing.
- Polycystic ovarian morphology (PCOM)
A characteristic ultrasound pattern and does not diagnose the syndrome by itself.
- Insulin resistance (IR)
Body tissues respond less effectively to insulin, so the body often compensates by producing more insulin.
- Dyslipidemia
An unfavorable lipid profile, often with higher triglycerides and lower High-Density Lipoprotein (HDL).
- Chronic low-grade inflammation
Persistent, modest immune activation, often tracked in studies with markers such as high-sensitivity C-Reactive Protein (hs-CRP).
- Sex Hormone-Binding Globulin (SHBG)
A blood protein that binds sex hormones. In human studies, lower SHBG can increase biologically active androgens.
- Luteinizing Hormone (LH)
A pituitary signal that regulates ovarian function; a relative excess of Luteinizing Hormone (LH) may favor androgen production and impaired follicle maturation.
- Follicle-Stimulating Hormone (FSH)
A pituitary signal that regulates ovarian function.
- High-Density Lipoprotein (HDL)
A lipid fraction often discussed as part of the lipid profile; in PMOS, dyslipidemia often includes lower High-Density Lipoprotein (HDL).
- high-sensitivity C-Reactive Protein (hs-CRP)
A marker used in studies to track chronic low-grade inflammation.
- Metabolically Healthy Obesity (MHO)
A phenotype used in research to distinguish people with obesity who have a relatively more favorable metabolic profile.
- Metabolically Unhealthy Obesity (MUO)
A phenotype used in research to distinguish people with obesity who have a less favorable metabolic profile, including higher inflammation, insulin resistance, liver fat markers, and cardiometabolic risk.
- Type 2 diabetes mellitus (T2DM)
A long-term metabolic disease involving impaired glucose regulation that is linked with PMOS in observational and follow-up studies.
- Metabolic syndrome (MetS)
A cluster of metabolic risk factors, such as elevated blood pressure, increased waist circumference, abnormal lipids, and impaired glucose regulation, associated with higher cardiometabolic burden.
- Visceral adiposity
Fat stored around internal abdominal organs; it is associated with higher cardiometabolic risk than body size alone.
- Gestational diabetes
A form of glucose dysregulation that occurs during pregnancy and is associated with PMOS in human studies.
- Preeclampsia
A pregnancy complication associated with PMOS in human studies, typically involving high blood pressure and systemic maternal risk.
- Gut microbiota dysbiosis
An imbalance in the gut microbial community that reviews associate with inflammation, insulin resistance, and androgen excess.
- Gut–metabolism–endocrine–ovary axis
An integrated biological framework describing interactions among the gut microbiota, metabolic pathways, endocrine signaling, and ovarian function.
- Treatment-naive
Describes patients who have not yet received treatment for the condition being studied.
- Homeostatic Model Assessment of Insulin Resistance (HOMA-IR)
An estimate of insulin resistance used in clinical studies.
- Visceral Adiposity Index (VAI)
A research index used to estimate visceral fat-related metabolic risk.
- Fatty Liver Index (FLI)
A research index used to estimate liver fat risk.
- Mediterranean Diet (MD) adherence
The degree to which a person’s eating pattern matches the Mediterranean Diet pattern used in research.
- Combined Oral Contraceptives (COCs)
Medications used as first-line treatment in many guidelines for menstrual irregularity and hyperandrogenic symptoms when pregnancy is not the immediate goal.
- Metformin
The most widely used insulin-sensitizing drug in PMOS. Human clinical evidence and broader reviews associate it with improved insulin sensitivity, lower circulating insulin and androgen levels, and better menstrual regularity.
- Insulin-sensitizing drug
A drug that helps the body respond better to insulin.
- Glucagon-Like Peptide-1 Receptor Agonists (GLP-1 receptor agonists)
Newer agents that have shown short-term metabolic and weight-related benefits in clinical settings, especially in obesity-associated PMOS.
- Thrombotic considerations
Concerns about blood clot risk that may apply to some hormonal therapies.
- Short-Chain Fatty Acids (SCFAs)
Microbiota-derived compounds proposed as mediators in the gut-metabolism-endocrine-ovary axis and linked with inflammation and insulin signaling.
- Branched-Chain Amino Acids (BCAAs)
Metabolites proposed as mediators in the gut-metabolism-endocrine-ovary axis and linked with metabolic regulation.
- Bile acids
Compounds proposed as mediators in the gut-metabolism-endocrine-ovary axis and linked with metabolic signaling.
- Lipopolysaccharide (LPS)
A molecule linked with inflammation and insulin resistance in gut-related PMOS mechanisms.
- Probiotics
Live microorganisms studied as microbiota-targeted strategies that may improve insulin resistance, dyslipidemia, or hyperandrogenism, though evidence remains limited.
- Prebiotics
Dietary compounds studied as microbiota-targeted strategies that may support beneficial gut microbes, though evidence remains limited.
- Inulin
A prebiotic fiber examined in limited human studies in relation to insulin resistance, dyslipidemia, or hyperandrogenism.
- Fecal Microbiota Transplantation (FMT)
A microbiota-targeted intervention supported mainly by animal work and lacking human outcome evidence here.
- Protein biomarkers
Circulating proteins being studied as possible diagnostic or stratification tools, though many remain early-stage and need validation across diverse populations.
- Machine learning (ML)
A computational approach used in research to build screening or diagnostic models from data.
- Deep learning (DL)
A subtype of machine learning used in research for pattern recognition, including diagnostic modeling.
- Diagnostic sensitivity
A measure of how well a test correctly identifies people who have a condition.
- Specificity
A measure of how well a test correctly identifies people who do not have a condition.
- Diagnostic odds ratio
A summary statistic used in diagnostic research to express how strongly a test distinguishes cases from non-cases.
- Summary receiver operating curve performance
A diagnostic research measure that summarizes test accuracy across thresholds.
- Phenotype A
The subgroup with oligo-anovulation, hyperandrogenism, and polycystic ovarian morphology (PCOM).
- Oligo-anovulation
Infrequent or absent ovulation.
- Case-control samples
A study design comparing people with a condition to people without it.
- External validation
Testing a diagnostic model or biomarker in independent populations outside the original study sample.
- Genetic susceptibility
An inherited tendency that may increase the likelihood of developing PMOS.
- Altered steroid production
Changes in the body’s hormone-making pathways that may contribute to PMOS biology.
- Epigenetic programming
Chemical changes around genes that can alter gene activity without changing the DNA (deoxyribonucleic acid) sequence itself.
- DNA (deoxyribonucleic acid)
The genetic material whose sequence is not changed by epigenetic programming.
- Prenatal androgen exposure
A proposed early-life influence in which androgen exposure before birth may bias later neuroendocrine, metabolic, and ovarian function in susceptible people.
- Neuroendocrine
Relating to interactions between the nervous system and hormone-producing systems.
- Life-course condition
A condition viewed as unfolding across the lifespan rather than only at one life stage.
- Observational studies
Studies that observe associations in people without assigning interventions, so they support association rather than certainty.
- Longitudinal cohorts
Groups of participants followed over time to study how early features relate to later outcomes.
- Hypothalamic-pituitary-ovarian axis
A hormone signaling system linking the brain and ovaries that helps regulate reproductive function.
- Adipose tissue dysfunction
Abnormal fat tissue biology that may contribute to metabolic strain and inflammation.
- Oxidative stress
A biologic state involving imbalance between damaging reactive molecules and the body’s defenses, discussed as part of PMOS mechanisms.
- Control loop
One change feeds another, then that second change reinforces the first.
- Mitochondria
The cell structures that help generate energy.
- Mitochondrial dysfunction
Impaired mitochondrial function, discussed in reviews as a possible contributor to oxidative stress and reduced metabolic flexibility.
- Metabolic flexibility
The body’s ability to adapt efficiently to changing energy demands and fuel sources.
- Vascular aging
Age-related deterioration in blood vessel health, potentially worsened by cumulative metabolic and inflammatory stress.
- Cardiometabolic burden
The combined strain on metabolic and cardiovascular systems, including risks related to glucose regulation, lipids, blood pressure, and adiposity.
- Cardiometabolic surveillance
Ongoing monitoring of metabolic and cardiovascular risk factors such as glucose, lipids, blood pressure, and central adiposity.
- Central adiposity
Excess fat stored around the abdomen, associated with higher cardiometabolic risk.
- Continuous metabolic syndrome severity z-score
A composite research measure used to track metabolic syndrome severity over time.
- Low-density lipoprotein (LDL)
A lipid fraction discussed in dyslipidemia; elevated levels are relevant to cardiovascular risk.
- Low-density lipoprotein cholesterol
A measured lipid outcome used in long-term cardiometabolic risk studies.
- High-density lipoprotein cholesterol
A measured lipid outcome used in long-term cardiometabolic risk studies.
- Triglycerides
A blood fat commonly elevated in PMOS-related dyslipidemia.
- Hirsutism
Excess coarse hair growth related to androgen excess.
- Myo-inositol
A nutraceutical examined in human trials as an early adjunct strategy, though evidence is not settled.
- Omega-3
A fatty acid supplement studied in human trials that may support lipids, though evidence is mixed.
- Vitamin D repletion
Correction of vitamin D deficiency, studied over 8 to 12 weeks; observed benefit may reflect correction of deficiency.
- Prebiotic fiber
A type of fiber used in early human work as a daily prebiotic intervention; gastrointestinal tolerance can vary.
- Polyphenol
A bioactive plant compound discussed in mechanistic and early human studies, though outcomes remain uncertain.
- Nutraceuticals
Supplement-like products such as myo-inositol, omega-3, or vitamin D used as adjuncts, though evidence is mixed and often short-term.
- Observer variation
Differences in interpretation between clinicians or researchers, especially relevant in ultrasound reading.
- Assay variability
Differences in laboratory measurement performance that can affect how hyperandrogenism is assessed biochemically.